Understanding Modern Urology Treatment: A Clinical Perspective on Diagnosis and Care
 Introduction
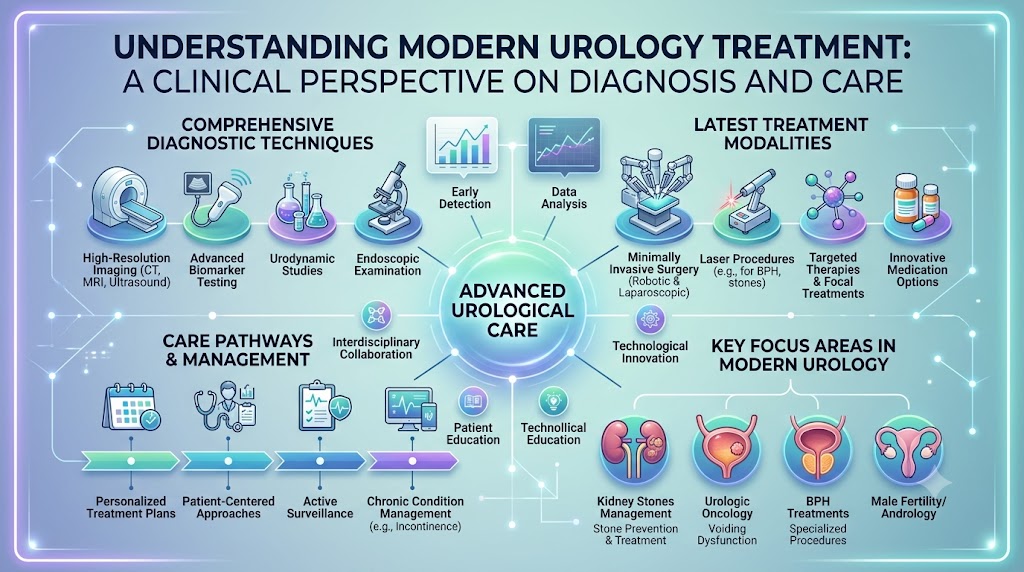
When a patient arrives at a clinic reporting urinary discomfort or flank pain, clinical care focuses on identifying the root physiological cause rather than simply suppressing individual symptoms. The urinary system—comprising the kidneys, ureters, bladder, and urethra—functions in close coordination with the male reproductive tract. Because even a slight obstruction or subtle inflammatory process can compromise systemic function, approaching these concerns through an objective medical lens is critical. Understanding the diagnostic thought process helps remove uncertainty from the patient experience, enabling individuals to engage in their health decisions with greater confidence. This guide provides a clinical perspective on urology treatment, outlining how conditions are accurately identified, how medical and surgical therapies are chosen, and how specialized hospitals support long-term recovery.
The Clinical Landscape of the Urological System
From a medical standpoint, the urological tract serves two essential biological purposes: filtering metabolic waste products from the bloodstream and maintaining fluid, electrolyte, and acid-base equilibrium. In male anatomy, it also integrates directly with reproductive structures, including the prostate, seminal vesicles, and testes.
Because these organs form a continuous, interconnected pathway, pathology in one segment frequently affects adjacent structures. A stone lodged within the narrow lumen of the ureter does not simply cause localized discomfort; it creates hydrostatic backpressure that can compromise renal parenchyma and impair kidney function. Likewise, tissue growth within the prostate gland constricts the prostatic urethra, challenging the detrusor muscle of the bladder and predisposing the individual to urinary stasis and recurring infections.
Clinical evaluation begins by isolating the anatomical site of dysfunction. Determining whether an issue originates in the renal filtration system, the urinary storage reservoir, or the outflow tract establishes the framework for subsequent diagnostic testing and therapy selection.
Clinical Presentation: Symptoms and Differential Considerations
Symptoms affecting the genitourinary system require structured differential assessment, as seemingly identical complaints can indicate fundamentally distinct pathologies.
- Altered voiding frequency and nocturia: Needing to void with unusual frequency throughout the day or night may suggest benign prostatic enlargement, detrusor overactivity, localized infection, or systemic metabolic changes such as uncontrolled diabetes.
- Dysuria and burning sensations: Discomfort during urination points toward mucosal inflammation, frequently stemming from bacterial pathogens, chemical irritation, or mechanical abrasion caused by passing crystals.
- Hematuria: The presence of erythrocytes in the urine—whether visible macroscopically or discovered under microscopic review—is a critical clinical sign that necessitates formal investigation to rule out stones, trauma, vascular anomalies, or cellular malignancy.
- Voiding dysfunction: Hesitancy, intermittent flow, straining, and the sensation of incomplete bladder emptying commonly indicate physical outflow obstruction or impaired bladder contractility.
- Urinary incontinence: Unintended loss of urine is clinically categorized into stress, urge, or overflow types, each requiring a different management strategy.
Because symptoms alone are rarely pathognomonic, clinicians rely on objective testing rather than assumptions to reach a definitive diagnosis.
Pathogenesis and Clinical Risk Factors
Developing a urological condition is typically the result of an interplay between anatomical vulnerabilities, genetic traits, and environmental exposures.
- Advancing age: Cellular proliferation in the prostate and progressive loss of tissue elasticity in the bladder occur naturally over decades, increasing the prevalence of voiding dysfunction.
- Fluid balance and hydration habits: Chronic sub-optimal hydration concentrates urinary solutes, accelerating the precipitation of calcium oxalate, uric acid, or phosphate crystals into symptomatic stones.
- Biological anatomy: The shorter female urethra creates a direct pathway for perineal flora to ascend toward the bladder, predisposing women to recurring bacterial colonization.
- Metabolic and vascular health: Systemic conditions such as atherosclerosis, hypertension, and diabetes mellitus can alter microvascular perfusion to the kidneys and impair pelvic autonomic nerve signaling.
- Carcinogenic exposure: Tobacco metabolites are processed by the kidneys and stored in the bladder, significantly increasing the long-term incidence of urothelial carcinomas.
Recognizing these risk factors allows clinicians to implement preventive strategies and adjust surveillance protocols appropriately.
The Diagnostic Pathway in Urology
Modern urology avoids speculative management, favoring targeted diagnostic pathways that verify pathology before invasive interventions are considered.
- Microscopic urinalysis and quantitative culture: Initial assessment of urine isolates red blood cells, leukocyte esterase, nitrites, and protein, while microbiological cultures identify specific pathogens and determine antibiotic sensitivity profiles.
- Renal function assays and serum markers: Blood biochemistry measures serum creatinine and estimated glomerular filtration rate to monitor kidney efficiency. Serum prostate-specific antigen testing provides an organ-specific indicator to aid clinical assessment when prostate pathology is suspected.
- Ultrasonography: High-frequency sound waves evaluate the renal parenchyma, screen for hydronephrosis, assess bladder wall thickness, and measure post-void residual urine volumes without exposure to ionizing radiation.
- Computed tomography and magnetic resonance imaging: Helical non-contrast CT remains the gold standard for identifying the size and location of urinary calculi. Contrast-enhanced CT and multiparametric MRI provide detailed anatomical resolution for soft-tissue masses and oncological staging.
- Diagnostic cystoscopy: Direct endoscopic visualization of the urethra, prostate, and urothelium allows physicians to identify structural strictures, stones, mucosal inflammation, and bladder tumors.
- Urodynamic evaluation: Advanced pressure-flow studies evaluate the complex mechanics of bladder storage and voiding pressures, assisting in the differentiation between bladder outlet obstruction and neurogenic bladder dysfunction.
Tiers of Urology Treatment
Medical decision-making in urology balances therapeutic effectiveness against procedural invasiveness, patient comorbidities, and recovery demands.
Conservative Surveillance and Behavioral Guidance
In situations where a condition poses no immediate physiological danger, watchful waiting combined with patient education is often the preferred strategy. Modifying fluid distribution throughout the day, eliminating bladder stimulants, and training pelvic floor musculature can resolve functional symptoms without pharmaceutical or surgical risks.
Pharmacotherapy
Medications are prescribed to alter physiological mechanics or target pathogens directly. Clinicians utilize alpha-blockers to relax smooth muscle tone at the bladder neck, 5-alpha-reductase inhibitors to reduce glandular prostate volume over time, antimuscarinics or beta-3 agonists to stabilize detrusor hyperactivity, and targeted antimicrobials to clear microbial infections.
Endoscopic and Minimally Invasive Interventions
Technological advancements have established minimally invasive techniques as standard therapies for many conditions. Utilizing natural anatomical pathways allows surgeons to fragment stones, ablate obstructing tissue, or remove early-stage lesions with minimal soft-tissue trauma, shorter hospitalizations, and faster functional recovery.
Reconstructive and Extirpative Surgery
When conservative and minimally invasive approaches are inadequate, open, laparoscopic, or robotic surgeries are employed. These procedures address severe architectural defects, manage large organ-confined tumors, and clear extensive obstructions.
Clinical Approaches to Major Urological Conditions
Kidney Stone Treatment
Renal and ureteral calculi require a management strategy dictated by stone composition, anatomical location, diameter, and patient symptomatology. Asymptomatic calculi smaller than 5 millimeters in the absence of infection often pass spontaneously with adequate hydration, pain relief, and medical expulsive therapy.
When a calculus causes persistent obstruction, unmanageable pain, or coexists with infection, active Kidney Stone Treatment is essential to protect kidney function. Extracorporeal shock wave lithotripsy delivers focused acoustic energy to fragment stones within the renal pelvis. Alternatively, ureteroscopy uses thin, flexible endoscopes and holmium or thulium lasers to pulverize stones directly within the ureter or kidney. For complex staghorn calculi, percutaneous nephrolithotomy creates a direct tract through the flank to break and extract stones safely.
Management of Prostate Conditions and Enlarged Prostate Treatment
Benign prostatic hyperplasia involves the non-malignant proliferation of epithelial and stromal cells in the transition zone of the prostate. When evaluating candidates for Enlarged Prostate Treatment, clinicians measure the impact on the patient's daily quality of life alongside quantitative objective metrics such as peak urinary flow rate and post-void residual volumes.
Medical management remains the first line of care for moderate symptoms. When obstruction progresses or urinary retention occurs, surgical and minimally invasive options are considered. Procedures such as transurethral resection of the prostate, laser enucleation, and water vapor thermal therapy remove or ablate obstructive tissue to restore urinary flow.
When malignancy is identified, Prostate Cancer Treatment is determined by histological grading via the Gleason score, clinical stage, PSA dynamics, and patient life expectancy. Low-risk, localized tumors are managed with active surveillance, monitoring the cancer closely to delay or avoid treatment-related side effects. Intermediate- and high-risk cases may require radical prostatectomy, external beam radiation therapy, brachytherapy, or systemic androgen deprivation therapy.
Urinary Tract Infection Treatment
Bacterial cystitis and pyelonephritis require accurate microbiological confirmation to avoid unnecessary prescribing. Targeted Urinary Tract Infection Treatment relies on antimicrobial sensitivity patterns identified in urine cultures.
Empirical antibiotic therapy should be refined as soon as laboratory sensitivities are available. Clinicians stress the necessity of completing the full course to prevent recurrence and limit antimicrobial resistance. In recurrent cases, clinicians evaluate the urinary tract for underlying anatomical abnormalities, foreign bodies, or urinary retention that could be shielding bacteria from standard therapy.
Evaluation and Management of Bladder Cancer
The hallmark sign of bladder cancer is painless, gross hematuria. The diagnostic standard combines cross-sectional upper-tract imaging with rigid or flexible cystoscopy to visualize suspicious mucosal lesions.
Subsequent Bladder Cancer Treatment depends entirely on whether neoplastic cells have penetrated the detrusor muscle. Non-muscle-invasive bladder cancer is managed with transurethral resection followed by intravesical chemotherapy or immunotherapy using Bacillus Calmette-Guérin to decrease recurrence rates. Muscle-invasive tumors require radical cystectomy with urinary diversion, often combined with neoadjuvant systemic chemotherapy or targeted radiation.
Principles of Robotic Urology Surgery
Modern surgical care frequently incorporates Robotic Urology Surgery for complex anatomical procedures, such as radical prostatectomy, partial nephrectomy, and radical cystectomy. The robotic platform translates the surgeon's hand movements into tremor-filtered, micro-articulated motions inside the patient, while high-definition 3D visualization improves tissue plane identification.
This technical precision aids in sparing neurovascular bundles and minimizing blood loss. However, robotic systems are tools operated by human surgeons; procedural success depends on surgical volume, team experience, and careful patient selection rather than the technology alone.
Evaluating Urology Hospitals and Specialists
Selecting appropriate care requires looking beyond general facilities to evaluate clinical infrastructure, subspecialty training, and institutional expertise. Specialized Urology Hospitals offer continuous clinical support, experienced operative teams, and comprehensive diagnostic equipment designed for complex urological interventions.
When evaluating care providers, key clinical considerations include:
- Subspecialty fellowship training: Complex conditions, such as advanced urologic malignancies or intricate pelvic floor disorders, benefit from care directed by fellowship-trained clinicians.
- On-site diagnostic infrastructure: Facilities equipped with immediate point-of-care ultrasound, flexible cystoscopy suites, and dedicated laboratory services provide faster, more coordinated diagnostic workflows.
- Volume and procedure specialization: Clinical outcomes generally correlate with institutional and provider case volumes for complex surgeries, including reconstructive interventions and partial nephrectomies.
- Multidisciplinary clinical collaboration: Optimal management of oncological or complicated reconstructive cases requires close coordination between urologists, medical oncologists, radiation oncologists, and nephrologists.
When patients search for a local Urologist Near Me, physical convenience must be balanced with whether the physician routinely manages the specific clinical condition in question. Choosing a provider based on clinical competence and appropriate hospital capabilities remains the most reliable path to achieving optimal health outcomes.
Practical Examples
Example 1: Clinical Triage of Acute Renal Colic
A 42-year-old patient presents to the emergency department with sudden, severe right flank pain radiating to the groin. A bedside focused ultrasound reveals mild right hydronephrosis. A subsequent low-dose non-contrast CT scan confirms a 4 mm stone in the distal ureter. Vital signs remain normal and the urine dipstick is negative for nitrites or infection. The clinical team explains that spontaneous passage occurs in a high percentage of small distal stones. The patient is discharged on oral hydration, an alpha-blocker to relax ureteral smooth muscle, and appropriate analgesics, with instructions to return immediately if fever or intractable vomiting occurs.
Example 2: Decision-Making in Progressive Bladder Outlet Obstruction
A 67-year-old man visits an outpatient clinic describing chronic nocturia, hesitancy, and a weak stream. An international prostate symptom score indicates moderate-to-severe symptoms. Physical examination notes benign prostatic enlargement, and an ultrasound measures a post-void residual volume of 180 mL with no upper-tract dilation. The physician presents the advantages and side-effect profiles of alpha-blockers versus 5-alpha-reductase inhibitors, while explaining available minimally invasive procedures. After considering personal lifestyle preferences, the patient chooses medical management and agrees to return for a repeat residual volume check in six weeks.
Decision-Making Framework
Step 1: Clinical Symptom Characterization
Document the onset, duration, and severity of symptoms, noting factors that aggravate or relieve the issue.
Step 2: Objective Diagnostic Evaluation
Undergo targeted testing, including lab assays and imaging, to establish a precise diagnosis before initiating therapy.
Step 3: Multi-Option Evaluation
Discuss all viable clinical approaches with your doctor, including watchful waiting, medications, and procedural options.
Step 4: Risk-Benefit Analysis
Weigh the potential side effects and recovery timelines of each intervention against its likelihood of clinical success.
Step 5: Facility and Specialist Selection
Select a specialist with verified training and a healthcare facility that offers the necessary infrastructure for your procedure.
Step 6: Follow-up and Surveillance Planning
Establish a clear post-treatment monitoring schedule to evaluate recovery and prevent future recurrence.
Common Mistakes to Avoid
- Dismissing transient hematuria: Painless blood in the urine must be thoroughly investigated, as bleeding can stop intermittently even when significant pathology persists.
- Empirical self-medication with antibiotics: Taking antibiotics without a culture can hide the true pathogen, fail to resolve the infection, and contribute to microbial resistance.
- Assuming lower urinary tract symptoms indicate only one condition: Frequent urination or hesitancy can stem from multiple distinct causes, requiring accurate differential testing.
- Ignoring chronic urinary retention: Untreated bladder outlet obstruction can lead to permanent detrusor muscle damage and progressive renal impairment.
- Focusing on surgical technology over surgeon volume: Advanced technologies are beneficial only in experienced surgical hands; technique and volume remain the primary drivers of success.
- Abandoning post-treatment surveillance: Skipping follow-up imaging or cystoscopy after stone removal or tumor resection risks missing asymptomatic recurrences.
Key Takeaways
- Early intervention preserves function: Timely evaluation of urinary changes prevents acute complications like urinary retention or kidney damage.
- Diagnostics drive care: Therapy should follow objective imaging and laboratory results rather than subjective symptom guesswork.
- Treatment is personalized: Modern urology provides a broad spectrum of care, from active monitoring to advanced surgical procedures.
- Anatomical factors guide choices: The size, location, and nature of the pathology dictate whether medication or surgery is the most appropriate step.
- Surgical experience matters: In complex interventions, the clinical experience of the surgeon and the hospital's capabilities are fundamental to achieving optimal outcomes.
- Follow-up is crucial: Long-term monitoring prevents recurrence and ensures that the urinary tract continues to heal and function normally.
Frequently Asked Questions
What does a urologist treat?
A urologist manages medical and surgical conditions affecting the urinary tract in both men and women, alongside the male reproductive organs. This includes stone disease, oncological conditions, benign prostatic hyperplasia, urinary incontinence, and male fertility.
When is it necessary to consult a urologist?
You should see a specialist if you experience persistent urinary symptoms, gross or microscopic blood in the urine, recurrent infections, sudden severe flank pain, or abnormal elevations in prostate-specific markers.
How do doctors diagnose kidney stones?
Diagnosis begins with a focused clinical history and urinalysis, followed by non-contrast computed tomography. Helical CT imaging confirms the stone's exact location, dimensions, and density, while ultrasound serves as a helpful radiation-free alternative for routine tracking.
When does a kidney stone require procedural intervention?
Procedural management is necessary when a stone is too large to pass spontaneously, causes intractable pain, creates persistent obstruction, or triggers an ascending urinary tract infection that threatens kidney function.
How does benign prostatic hyperplasia differ from prostate cancer?
Benign prostatic hyperplasia is a non-cancerous cellular growth in the central transition zone of the prostate that constricts urine flow. Prostate cancer involves malignant transformation, typically in the peripheral zone, requiring distinct diagnostic and therapeutic pathways.
How do clinicians confirm a urinary tract infection?
Confirmation relies on evaluating symptoms alongside microscopic urinalysis and quantitative urine culture. The culture identifies the bacterial species and provides an antibiotic sensitivity profile to ensure effective, targeted prescribing.
What is robotic urology surgery?
Robotic surgery is a minimally invasive technique where the surgeon operates wristed instruments via a computer console. The platform provides magnified three-dimensional visualization and high precision for complex operations on the prostate, kidneys, or bladder.
Is robotic surgery superior to standard surgical techniques?
While robotic surgery often reduces blood loss and hospital recovery times in select cases, overall clinical outcomes depend heavily on the surgeon's training, experience, and appropriate patient selection rather than the machine itself.
How can patients evaluate a urology specialist?
Review the physician's subspecialty fellowship credentials, verify board certification, assess procedure-specific surgical volumes, and ensure their affiliated hospital offers dedicated urological diagnostic and surgical infrastructure.
What should I ask during an initial urological consultation?
Inquire about the underlying causes of your symptoms, which diagnostic evaluations are necessary, the comparative risks and benefits of available treatment options, and the expected recovery or monitoring timeline.
Conclusion
Navigating genitourinary health requires moving past subjective assumptions to rely on structured clinical evaluation. Urological conditions—whether involving acute stone obstruction, chronic lower urinary tract symptoms, or complex oncological diagnoses—respond best to care tailored to the patient's specific anatomy and general health. Modern medicine offers diverse therapeutic options, from active surveillance and pharmacological interventions to minimally invasive procedures and robotic-assisted surgeries. Obtaining an objective, accurate diagnosis through proper laboratory work and imaging is the foundation of effective management. By consulting experienced specialists, evaluating hospital capabilities, and remaining engaged in the decision-making process, patients can approach their care with clarity, realistic expectations, and confidence.